Dental Emergency and Oral Trauma: A Beginner’s Guide
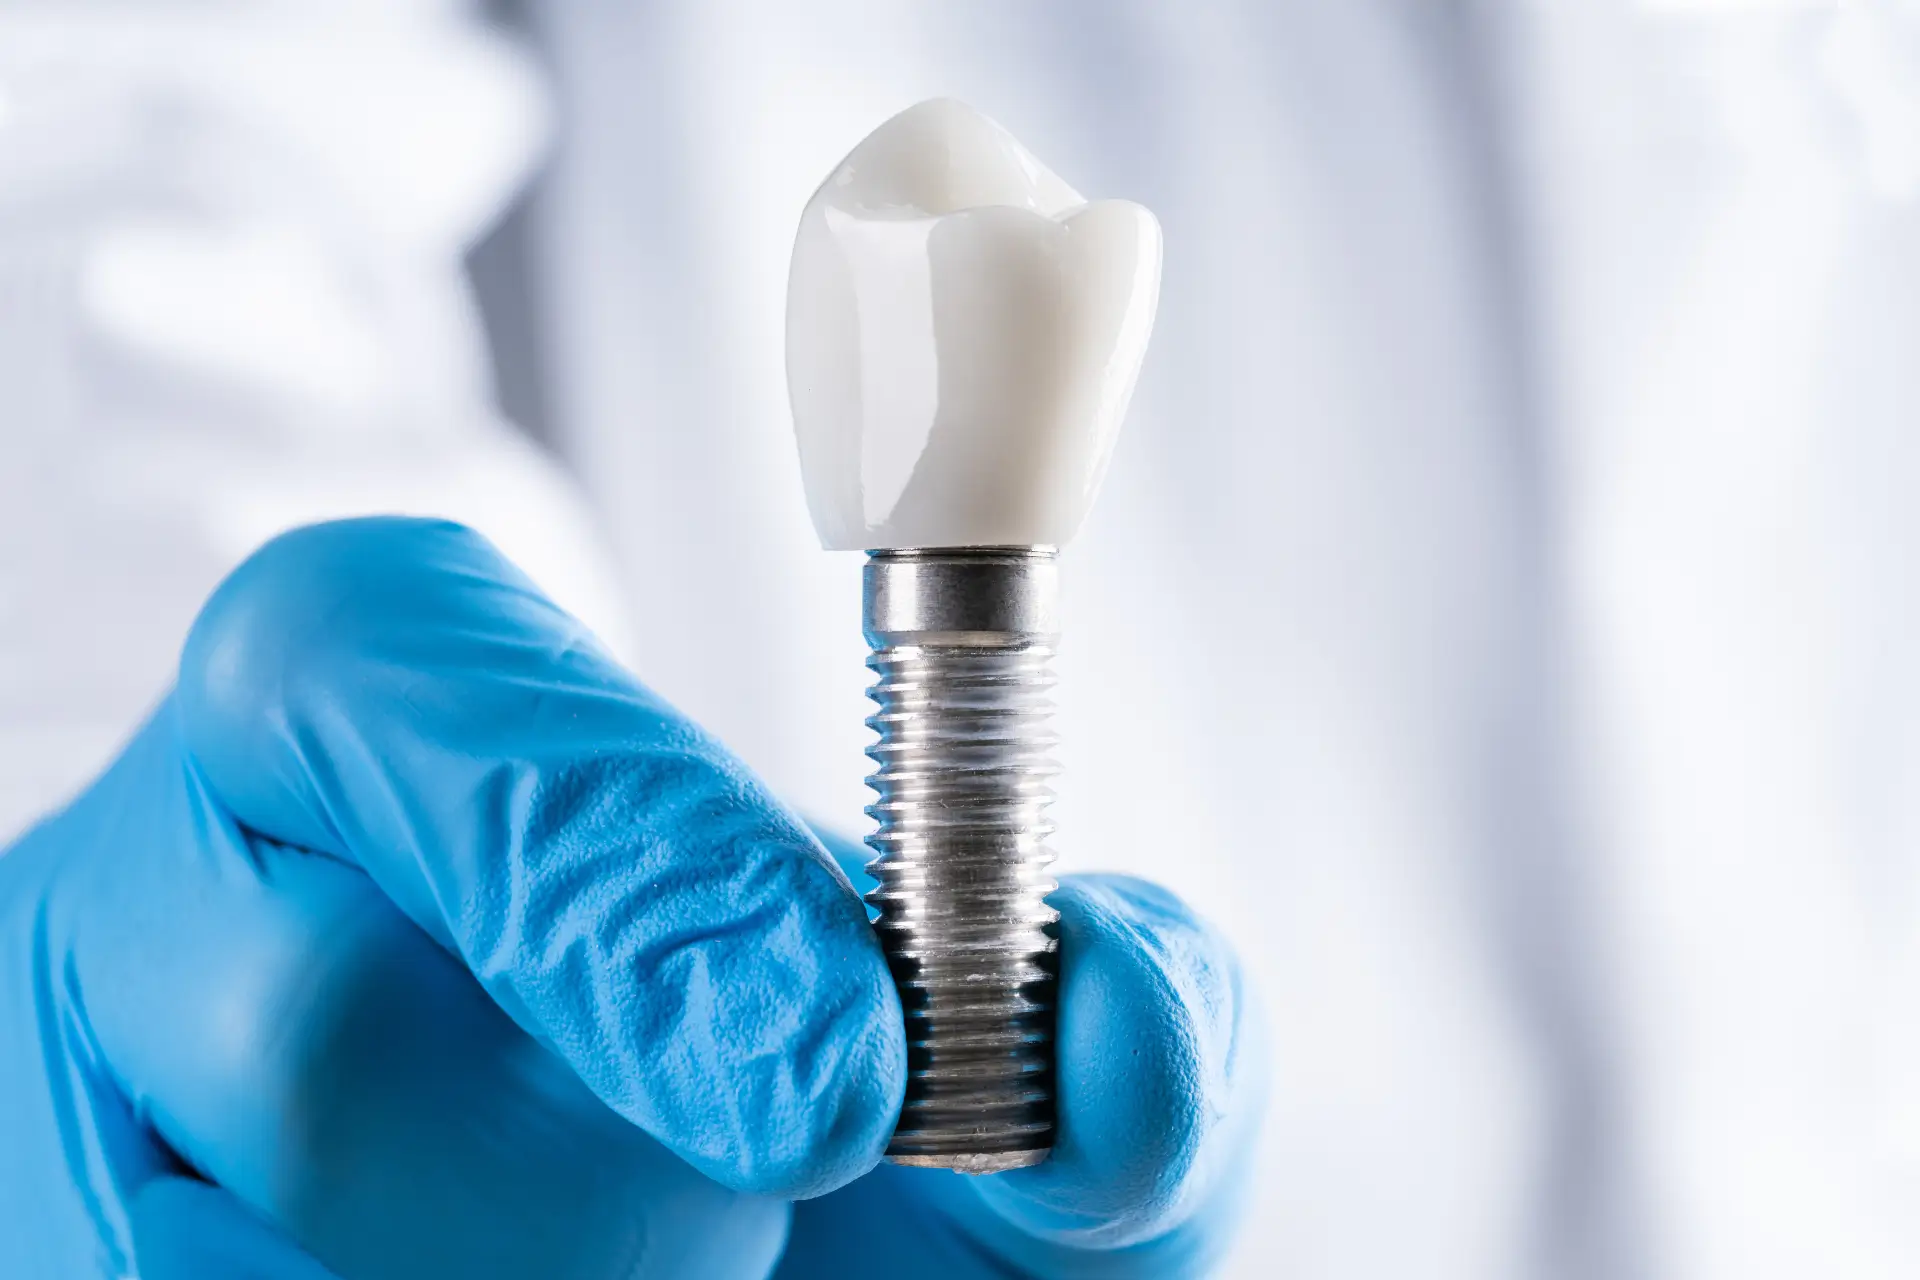

A true dental emergency rarely arrives at a convenient hour. It tends to happen during dinner, on a sports field, in a parking lot, or right before a holiday weekend when every office seems to be closed. What makes these situations stressful is not only the pain. It is the uncertainty. People often do not know whether they are dealing with a problem that can wait until morning or one that needs immediate care.
Oral trauma and sudden dental pain sit in an awkward category. They can look dramatic and still turn out to be manageable, or they can seem minor at first and worsen quickly. A chipped tooth may expose the nerve. A small cut in the mouth may bleed heavily because oral tissues are richly supplied with blood. A tooth that appears only slightly loose after a fall may later die because its blood supply was damaged. The first few decisions matter.
This guide is meant to make those first decisions easier. It will help you recognize common emergencies, take useful first-aid steps, and understand what a dentist is trying to prevent when they say, “Come in now.”
What counts as a dental emergency
Not every tooth problem is an emergency, even if it is unpleasant. A lost filling on a molar that is not painful can often wait a day or two. Mild sensitivity to cold usually does not require urgent treatment. On the other hand, uncontrolled bleeding, facial swelling, severe pain, a knocked-out tooth, or an injury that affects breathing or swallowing should be treated as urgent.
A practical way to think about a Dental Emergency is to ask three questions. Is there heavy bleeding? Is there severe pain or swelling? Is there a risk of losing a tooth or spreading infection? If the answer to any of those is yes, you should contact a dentist promptly, and in some situations go straight to an emergency department.
Timing also matters more than many people realize. A knocked-out permanent tooth has the best chance of being saved if it is replanted quickly, ideally within 30 minutes, though dentists still try beyond that window depending on how the tooth was stored. Deep infections can move from a painful tooth into facial spaces, and those infections can become serious fast. Early action is often less invasive, less expensive, and much more predictable.
The kinds of oral trauma dentists see most often
Oral trauma covers a broad range of injuries. In practice, the most common involve broken teeth, displaced teeth, lip and gum lacerations, jaw pain after a blow, and soft tissue bruising. Children often present after falls. Teenagers and adults show up after sports injuries, bicycle accidents, playground mishaps, or biting unexpectedly hard into something like olive pits, bones, or unpopped popcorn kernels.
Front teeth are especially vulnerable. They sit forward in the mouth and take the hit in a face-first fall. A small enamel chip can be mostly cosmetic, but larger fractures may expose dentin, which is the yellowish layer under enamel, or even the pulp, where the nerve and blood vessels live. Once the pulp is involved, pain usually intensifies, and the tooth’s long-term survival becomes more uncertain.
Back teeth tell a different story. Molars and premolars are thick and strong, but they crack under compressive forces. A person may feel a sharp pain on biting, release pressure, and then wonder whether they really need to be seen. The answer depends on symptoms, but a crack can travel in ways that are hard to predict. Waiting too long can turn a restorable tooth into one that needs root canal treatment or extraction.
Soft tissue injuries can look alarming. The mouth bleeds dramatically because the tissues are delicate and highly vascular. A cut lip, torn frenum, or bitten cheek can produce a lot of blood with relatively little long-term damage. That said, deep Dental Emergency lacerations, embedded debris, or cuts that cross the border of the lip often need professional assessment and sometimes sutures.
First priorities in the first ten minutes
When an injury happens, people naturally focus on the tooth they can see. A better first move is to step back and assess the whole person. If there was a significant blow to the face, loss of consciousness, dizziness, confusion, vomiting, trouble breathing, or suspected jaw fracture, medical evaluation takes priority over dental treatment. Teeth matter, but airway and head injury matter more.
If the situation appears limited to the mouth, your goals are simple: control bleeding, reduce swelling, protect the injured area, and preserve anything that may be reattached or replanted. Clean hands help. Gentle pressure with clean gauze is usually the fastest way to control bleeding from gums or lips. A cold compress on the outside of the face can reduce swelling and numb discomfort. Rinsing with water helps clear blood so you can see the injury more accurately.
Here are the immediate steps that are most useful in a typical Dental Emergency involving trauma:
- Stay calm and check for more serious injury first, especially head trauma, breathing difficulty, or a possible broken jaw.
- Control bleeding with firm but gentle pressure using clean gauze or a clean cloth for about 10 minutes without repeatedly checking.
- Find any broken tooth fragment or the whole tooth, hold it by the crown rather than the root, and rinse it briefly with milk or saline if dirty.
- Contact a dentist as soon as possible, and if a permanent tooth has been knocked out, ask whether it should be replanted immediately.
- Use a cold compress and avoid eating, drinking very hot liquids, or chewing on the injured side until you are examined.
That short window after an accident is often when teeth are most salvageable. It is also when well-meaning mistakes happen. Scrubbing a knocked-out tooth, wrapping it in tissue, letting it dry on a counter, or giving a numb child something hard to chew are all common errors.
The knocked-out tooth, where minutes matter
A knocked-out permanent tooth is one of the clearest dental emergencies in all of dentistry. The technical term is avulsion. In plain language, the entire tooth has come out of the socket. This is a race against time because the cells on the root surface begin to die when they dry out.
If the tooth is a permanent tooth, not a baby tooth, pick it up by the crown. That is the chewing or visible part. Avoid touching the root if possible. If it is visibly dirty, rinse it very gently for a few seconds in milk or saline. Water is acceptable if there is nothing else, but prolonged soaking in plain water is not ideal. If the person is alert and cooperative, and there is no major injury preventing it, the best option may be to place the tooth back into the socket right away and have the patient bite gently on gauze to hold it there. This can feel intimidating, but it is often the move that gives the tooth the best chance.
If replanting is not possible, store the tooth in cold milk or in a tooth preservation kit if one is available. Some people place the tooth in the person’s cheek, but that is not a great option for children or anyone who may swallow it. Then get to a dentist immediately.
Baby teeth are different. They generally should not be replanted because of the risk of damaging the developing permanent tooth underneath. This distinction matters. Parents are often distressed when a small front baby tooth is lost in a fall, but putting it back is not the right response.
Broken, chipped, and cracked teeth
The word “broken” covers injuries with very different consequences. A tiny chip in enamel may need smoothing or bonding and little else. A larger break can expose dentin and make the tooth sharply sensitive to cold air or water. If the pulp is exposed, the center of the tooth may look pink or red, and pain can be strong, throbbing, or triggered by temperature.
One useful habit is to save the broken fragment if you can find it. Dentists sometimes reattach pieces, especially on front teeth. Even when reattachment is not possible, the fragment can help identify the size and shape of the missing area.
Cracks deserve respect because they are not always visible. A patient may say, “It only hurts when I bite a certain way,” or “The pain zings and then disappears.” That pattern can signal a crack running through the tooth. The challenge is that some cracks are superficial and manageable, while others extend deep below the gumline and compromise the tooth permanently. The earlier a dentist can evaluate it with magnification, percussion tests, and imaging, the more treatment options there usually are.
A practical detail many people miss is that a cracked tooth is vulnerable after the first injury. Chewing a bagel crust, nuts, or ice on that side can turn a repairable crack into a split tooth. Soft foods and chewing on the opposite side are sensible until you are seen.
When swelling is the real danger
Pain gets attention. Swelling deserves just as much. Facial swelling can result from trauma, infection, or both. After a blow to the mouth, swelling may be straightforward bruising. After a toothache that has been brewing for a few days, swelling may signal Dental Emergency infection spreading beyond the tooth.
Not every dental infection is immediately dangerous, but some absolutely are. Warning signs include rapidly increasing swelling, difficulty opening the mouth, fever, foul-tasting drainage, trouble swallowing, trouble breathing, or swelling that extends toward the eye or down into the neck. Those situations need urgent care, sometimes in a hospital rather than a dental office.
A common mistake is trying to “ride out” a swollen tooth with leftover antibiotics, clove oil, or pain medicine alone. Antibiotics can be appropriate, but they are not the full treatment for many dental infections. If the source is an infected pulp or abscessed tooth, the pressure often needs to be relieved through drainage, root canal treatment, or extraction. Without source control, symptoms may settle and then return worse.
Bleeding from the mouth, what is normal and what is not
Mouth injuries bleed in a way that can look disproportionate. A small gum tear may mix with saliva and seem dramatic. Usually, steady pressure solves the problem. The key is steady. People often remove the gauze every 20 seconds to check, which interrupts clot formation and restarts the cycle.
If bleeding continues despite 10 to 15 minutes of uninterrupted pressure, if blood is pooling quickly, or if the person takes blood thinners and the bleeding seems difficult to control, seek care urgently. The same applies if there is a deep cut, visible fat, or a laceration that distorts the lip border.
Teeth can also bleed from the socket after extraction or trauma. A small amount of oozing is common. Bright red, active bleeding that soaks through gauze repeatedly is not. In those cases, firm pressure and prompt guidance from a dentist are appropriate.
Children, sports, and the special rules of baby teeth
Children produce a lot of anxiety around oral injuries because their mouths are changing. A five-year-old who falls off a scooter may damage a baby tooth, the gum, and the developing adult tooth bud all at once. The good news is that children often heal well. The tricky part is knowing what not to do.
If a baby tooth is pushed out of position, fractured, or knocked out, a dentist should still assess it. The goals are pain control, protection of the soft tissues, and monitoring for effects on the permanent successor. Occasionally the safest path is simply observation. Other times the baby tooth needs smoothing, extraction, or follow-up imaging. A darkening baby tooth after trauma can indicate pulpal changes, but not every color change demands immediate treatment. These are judgment calls where an experienced pediatric dentist adds real value.
Sports injuries are a category where prevention matters almost as much as treatment. Custom or well-fitted boil-and-bite mouthguards reduce the risk of broken and displaced teeth significantly. They do not eliminate concussion risk, but they absolutely help with dental trauma. I have seen families spend thousands repairing front teeth after one elbow during a basketball game, then finally buy the mouthguard they had postponed over a modest inconvenience.
Jaw injury, bite changes, and signs something deeper is wrong
A person may walk away from a facial injury focused on a chipped tooth when the bigger problem is a jaw injury. Clues include difficulty opening or closing fully, the teeth no longer fitting together properly, numbness in the lower lip or chin, pain just in front of the ear, or a sense that the jaw shifts when moving.
A fracture is not always obvious externally. Swelling and bruising can mask it. If the bite feels suddenly “off,” that is meaningful. Dentists and oral surgeons pay close attention to bite changes because the teeth act like a built-in alignment guide. When they do not meet as they did before the accident, deeper structures may be involved.
Emergency departments can assess facial fractures, but depending on the setting, a maxillofacial surgeon may still be needed for definitive care. This is one of those situations where a dental issue crosses into broader trauma management.
Pain relief at home, what helps and what creates problems
People in a Dental Emergency usually want one thing first: the pain to stop. Over-the-counter pain relievers can help, but they work best when used appropriately and within label directions. For many adults, ibuprofen can be effective for dental pain because it reduces inflammation, though it is not suitable for everyone, particularly people with certain stomach, kidney, bleeding, or medication issues. Acetaminophen may be safer in some of those cases. Dentists often recommend specific combinations or schedules, but that advice should be individualized.
What does not help much is placing aspirin directly on the gum or tooth. This old home remedy can actually burn the soft tissue and make matters worse. Very hot or very cold foods often aggravate an injured tooth, as does chewing on it repeatedly to “test” whether it still hurts. Leave the testing to the exam.
If there is swelling from trauma, cold is useful in the first day. If the source is infection, cold may still soothe discomfort, but it does not treat the cause. Saltwater rinses can be comforting after some injuries, provided they are gentle and not so vigorous that they disturb clots or sensitive tissues.
What the dentist is likely to do when you arrive
One reason people delay care is fear of the unknown. It helps to know what an emergency visit usually involves. The first step is a focused history: how the injury happened, when it happened, where the pain is, whether there was loss of consciousness, and whether the tooth was dry or stored in anything. That timeline matters a great deal.
The exam often includes checking tooth mobility, tapping on the teeth, assessing the bite, testing temperature sensitivity, and looking for cuts, bruises, and swelling patterns. Dental radiographs are common, and in some trauma cases additional imaging may be needed. The first appointment may not solve everything permanently. Sometimes the immediate goal is stabilization, pain relief, protection of the pulp, repositioning a displaced tooth, or placing a splint, with definitive repair scheduled after the tissues settle.
Here is what that care may look like in common situations:
| injury | likely same-day treatment | | --- | --- | | knocked-out permanent tooth | replantation if possible, splinting, follow-up planning | | displaced or loose tooth | repositioning, splinting, imaging, monitoring pulp vitality | | chipped front tooth | smoothing, bonding, temporary protection, possible fragment reattachment | | deep fracture with nerve involvement | pulpal protection, root canal planning, temporary build-up or extraction discussion | | soft tissue laceration | cleaning, checking for embedded fragments, possible sutures |
Follow-up is part of trauma care, not an optional extra. Teeth that look stable on day one can change over weeks or months. Nerves may die later. Roots can resorb. Color can shift. This is why dentists often recheck traumatized teeth at intervals instead of declaring them “fine” after one visit.
The gray zone, urgent but not middle-of-the-night urgent
A lot of dental problems live in the gray zone. They hurt, they matter, but they may not justify waking an on-call team at 2 a.m. A crown that fell off without pain, a dull toothache that responds to medication, or a chipped tooth with no sensitivity often falls into this category. That does not mean ignore it. It means call first thing, protect the area, and avoid making it worse.
By contrast, severe pain that keeps escalating, swelling, trauma with a loose or displaced tooth, significant bleeding, or any sign of infection spreading should move to the front of the line. When people ask whether they are “overreacting,” my general view is that it is better to call and be told it can wait than to stay home while a manageable problem becomes a more complicated one.
Prevention that actually changes outcomes
Many emergencies are not preventable. Falls happen. People slip on stairs. Accidents remain accidents. Still, a surprising number of urgent visits trace back to repeatable patterns. Grinding weakens teeth over time. Untreated cavities undermine tooth structure until a routine bite snaps a cusp. No mouthguard during contact sports leaves the front teeth exposed.
The most effective preventive habits are not glamorous. Routine dental care catches cracks, failing fillings, and deep decay before they turn into weekend pain. Mouthguards for sports work. Seatbelts work. Avoiding chewing ice, hard candy, and popcorn kernels saves more molars than people realize. If you have a history of clenching or grinding, a well-made night guard can reduce the risk of fractures.
Parents can also prepare by knowing where to call after hours and keeping a small dental first-aid kit at home with gauze, a clean container, and saline. That kind of preparation feels unnecessary right up until the night it becomes priceless.
Knowing when to escalate to emergency medical care
A dentist is the right professional for many urgent oral problems, but not all. If there is difficulty breathing, trouble swallowing, altered mental status, heavy uncontrolled bleeding, suspected facial fracture with functional problems, or a significant head injury, emergency medical care comes first. The same goes for rapidly spreading swelling accompanied by fever or signs of systemic illness.
This can be frustrating for patients who want “just the tooth fixed,” but the mouth is not separate from the rest of the body. Serious infections and major trauma do not respect that boundary. The safest care is the care that matches the actual risk in front of you.
Most of the time, though, a dental emergency becomes far less overwhelming once you know the basic rules. Protect the person first. Preserve the tooth correctly. Control bleeding with steady pressure. Do not ignore swelling. Get expert eyes on the injury sooner rather than later. Those steps will not make the event pleasant, but they do improve the odds that pain, function, and appearance can be restored with less trouble than you might fear in the moment.
Vitality Dental
Address: 1220 Coit Rd #106, Plano, TX 75075
Phone number: +19726454100
FAQ About Dental Emergency
What can the ER do for a tooth?
An emergency room (ER) can manage pain and treat severe infections with medication, but it cannot fix or pull a tooth.
What is considered a dental emergency?
A dental emergency is any oral health problem that involves severe pain, uncontrollable bleeding, or an infection that threatens your health or requires immediate care to save a tooth.
Is there a 24-hour dental service in Plano, TX?
There is no physical dental clinic in Plano, Texas, that stays open with walk-in staff 24 hours a day, but several offices offer 24/7 phone support, late-night hours, or same-day emergency care.